Evidence-Based HRT Treatment Options: A 2026 Guide
The Hot Flush FilesTable of Contents
- What Is Hormone Replacement Therapy and Menopausal Hormone Therapy?
- HRT Patches vs Tablets: Delivery Methods Explained
- HRT for Perimenopause Symptoms: Which Treatment Addresses What
- HRT Benefits and Risks: What the Evidence Shows
- Estrogen-Only vs Combined Hormone Therapy: Which Is Right for You?
- Questions to Ask Your Doctor About HRT
- Monitoring Your Treatment and When to Review Your Plan
- Frequently Asked Questions
Last Updated: October 12, 2026
What Is Hormone Replacement Therapy and Menopausal Hormone Therapy?
Understanding HRT treatment options means grasping the fundamental difference between systemic therapy and local treatment. Systemic therapy delivers hormones throughout your body via tablets, patches, gels, or sprays, addressing widespread symptoms.
At UnPause, our team of AHPRA-registered menopause experts works with you to determine whether HRT is appropriate for your individual situation, your symptom profile, and your medical history. Evidence-based HRT treatment options vary widely, and what works for one woman may not suit another.
HRT Patches vs Tablets: Delivery Methods Explained
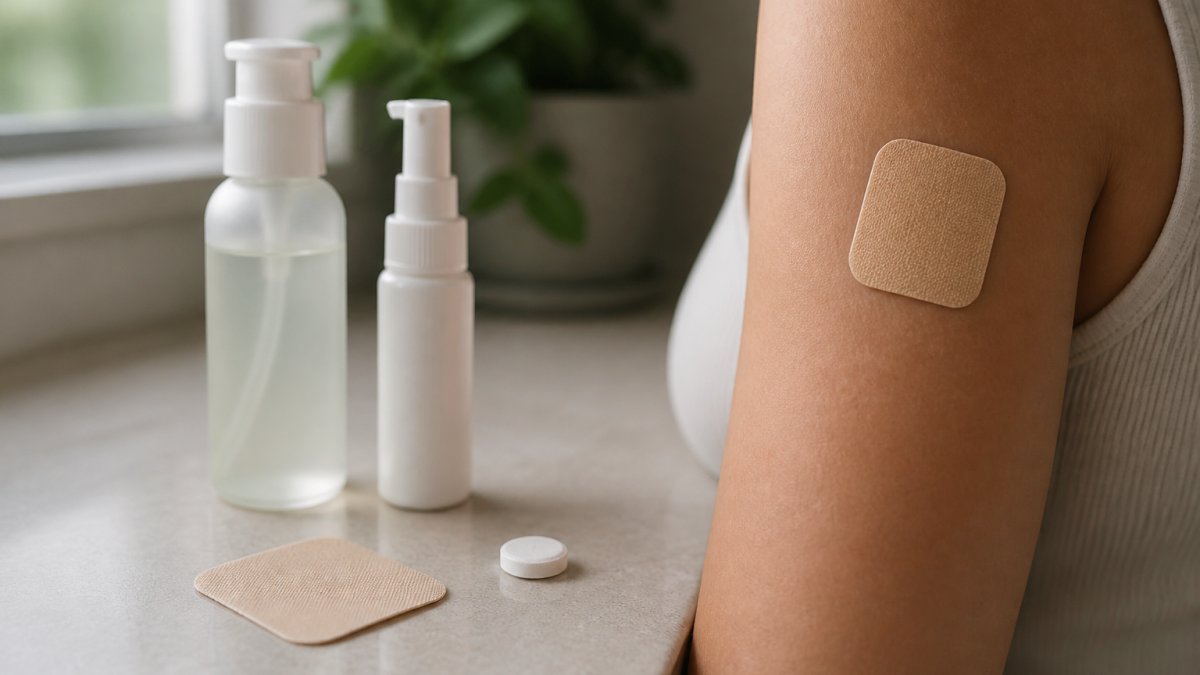
The delivery method you choose affects how your body absorbs hormones, how quickly you feel relief, and how well you tolerate the treatment. Three main categories dominate: oral formulations, transdermal methods (patches, gels, sprays), and vaginal or local treatments.
Tablets and oral formulations
Tablets are the most commonly prescribed HRT treatment option, partly due to familiarity and cost. They're taken daily and absorbed through your digestive system.
This route has both advantages and limitations. Tablets are convenient, portable, and don't require application technique. However, they can increase blood clotting factors and may affect liver function markers. Some women experience nausea when taking tablets, particularly if taken on an empty stomach.
Continuous regimens (same dose daily) suit most women, while sequential or cyclical regimens (varying doses across the month) mimic a more natural cycle and may reduce breakthrough bleeding. Your menopause expert will discuss which approach aligns with your preferences and symptom pattern.
Patches, gels, and sprays
Transdermal methods bypass your digestive system entirely, delivering hormones directly through your skin into your bloodstream. This approach avoids first-pass metabolism, which means lower effective doses often provide equivalent symptom relief compared to tablets.
Patches are typically changed once or twice weekly depending on the formulation. They're discreet, consistent in delivery, and suitable for women who experience nausea with oral medications or have liver concerns.
Gels and sprays offer daily application with flexible dosing. You can adjust the amount you apply to fine-tune your hormone levels. Many women find gels and sprays feel less "medical" than patches, though application technique matters for consistent absorption.
Vaginal and local treatments
Vaginal estrogen creams, tablets, and rings deliver high concentrations of estrogen directly to vaginal tissue with minimal systemic absorption. These are ideal for genitourinary symptoms, vaginal dryness, painful intercourse, urinary urgency, without addressing hot flushes or night sweats.
Many women use vaginal estrogen alongside systemic HRT, or as a standalone treatment if systemic therapy isn't appropriate. Vaginal moisturisers and lubricants offer non-hormonal alternatives for dryness, though they don't address underlying tissue changes.
HRT for Perimenopause Symptoms: Which Treatment Addresses What
Different symptoms respond to different HRT treatment options.
Mood changes, brain fog, and anxiety during perimenopause involve both estrogen and progesterone fluctuations. Systemic HRT addresses these, though the timing of progesterone matters.
Vaginal dryness, painful intercourse, and urinary symptoms may improve with systemic HRT alone, but often require local vaginal estrogen for complete relief.
Sleep disruption during perimenopause stems from night sweats, hormonal shifts, and sometimes mood changes. Systemic HRT typically improves sleep quality within weeks.
Joint and muscle aches associated with the menopausal transition respond to systemic HRT in many women, though the mechanism isn't fully understood.
HRT Benefits and Risks: What the Evidence Shows
Proven benefits of hormone therapy
The evidence for HRT's effectiveness in relieving menopausal symptoms is strong. Systemic HRT significantly reduces hot flushes and night sweats in most women within 2-4 weeks.
Beyond symptom relief, HRT offers bone health benefits. Estrogen slows bone loss after menopause, reducing fracture risk, a concern for many women as they age.
Cardiovascular and cognitive outcomes are more nuanced. Recent evidence suggests HRT does not increase heart disease risk in women who start treatment close to menopause onset (within 5-8 years of final menstrual period).
Quality of life improvements are profound. Women on effective HRT report better sleep, improved mood, clearer thinking, and restored sense of wellbeing.
Known risks and side effects
Early HRT research raised concerns about breast cancer risk, particularly with combined estrogen-progestogen therapy used long-term. Current evidence indicates the risk is modest and largely reversible after stopping treatment.
Venous thromboembolism (blood clots) risk is slightly elevated with oral estrogen due to first-pass liver metabolism.
Vaginal bleeding can occur, particularly during the first few months of HRT. Sequential regimens trigger monthly bleeding patterns, while continuous combined regimens typically eliminate bleeding. Unexpected bleeding warrants review by your menopause expert to ensure appropriate dosing.
Breast tenderness, headaches, and nausea occur in some women, particularly in the first weeks of treatment. These side effects often settle within 4-6 weeks.
Estrogen-Only vs Combined Hormone Therapy: Which Is Right for You?
Estrogen-only HRT contains estrogen alone, while combined HRT includes both estrogen and progestogen. The choice depends on your uterus status and symptom profile.
Women who've had a hysterectomy (uterus removed) use estrogen-only therapy because there's no uterine lining to protect.
The progestogen component matters. Synthetic progestogens (medroxyprogesterone, norethisterone) work effectively but carry different side effect profiles than body-identical progesterone.
Combined HRT comes in two regimens: sequential (progestogen added for 10-12 days monthly, triggering withdrawal bleeding) and continuous (both hormones daily, typically eliminating bleeding).
Estrogen-only therapy allows higher estrogen doses without endometrial risk, which can be advantageous for severe symptoms. However, estrogen-only users must maintain regular gynaecological surveillance.
Questions to Ask Your Doctor About HRT
Before starting any HRT treatment option, clarify these essential points with your menopause expert:
About your individual situation: What's driving my symptoms? Are they typical for perimenopause or could something else explain them? Do I have any medical conditions or medications that affect which HRT type is safest for me?
About HRT itself: Why are you recommending this particular HRT treatment option for me? What dose are we starting with, and why? How long until I should expect to feel better?
About monitoring: How often will we review how I'm responding? What changes in symptoms or side effects warrant a dose adjustment? When should I contact you between appointments?
About duration: How long do you typically recommend staying on HRT? What does stopping look like, do we taper gradually or stop suddenly?
About alternatives: If HRT doesn't work or I can't tolerate it, what other options exist? Are there non-hormonal medications or lifestyle approaches that might help?
About your approach: How do you stay current with menopause evidence?
At UnPause, our AHPRA-registered menopause experts prioritise these conversations.
Monitoring Your Treatment and When to Review Your Plan
Effective HRT requires follow-up. After starting treatment, schedule a review within 4-6 weeks to assess symptom response and side effects.
If your symptoms aren't adequately controlled, your dose may need adjustment. Small increases often make a significant difference.
Annual reviews are standard once you're on a stable regimen.
Bone density screening (DEXA scan) is typically recommended for women on HRT, particularly if you have risk factors for osteoporosis.
Breakthrough bleeding, unexpected bleeding on continuous combined HRT, warrants investigation.
If HRT stops working after months of stability, discuss this with your menopause expert.
Navigating HRT treatment options can feel overwhelming when you're managing disruptive symptoms and conflicting advice.
UnPause connects you with AHPRA-registered menopause experts who listen, explain the evidence, and work with you to find the right HRT treatment option.
Frequently Asked Questions
What is the safest HRT treatment option for perimenopause?
Safety depends on your individual medical history, symptoms, and risk factors. Transdermal estrogen (patches, gels, sprays) is often considered a lower-risk option than oral tablets because it bypasses the liver and avoids first-pass metabolism. Combined estrogen-progestogen therapy is safer than estrogen-only therapy for women with an intact uterus. The safest HRT treatment option is the one your menopause expert tailors to your specific circumstances after a thorough health assessment. Our team of AHPRA-registered doctors at UnPause specialises in this individualised approach.
How do I choose between HRT patches, gels, and tablets?
Your choice depends on symptom severity, lifestyle, absorption preferences, and medical history. Tablets suit women who want simplicity and don't mind daily dosing. Patches, gels, and sprays offer steady hormone delivery without daily administration and are preferred if you have liver concerns or poor tablet absorption. Gels and sprays allow flexible dosing adjustments. Patches provide consistent, tamper-proof delivery. Discuss your daily routine, preferences, and any contraindications with your menopause expert to find the best fit for your life.
What are the main benefits and risks of HRT?
HRT effectively relieves hot flushes, night sweats, vaginal dryness, sleep disruption, and mood changes for most women. It also helps prevent bone loss and fractures during and after menopause. Short-term risks include breast tenderness, bloating, and nausea (often resolve within weeks). Long-term risks vary by type, dose, duration, and individual factors; combined estrogen-progestogen therapy carries a slightly elevated risk of breast cancer and blood clots compared to estrogen-only therapy, though absolute risks remain low. Your menopause expert will weigh these against your symptom burden and personal risk profile.
Who should avoid HRT or use it with caution?
HRT is not suitable for women with a history of hormone-sensitive breast cancer, untreated high blood pressure, or active blood clots. Caution is advised for women with a strong family history of breast cancer, migraine with aura, liver disease, or undiagnosed vaginal bleeding. Some women can use HRT safely with closer monitoring or adjusted regimens. Your menopause expert will review your full medical history, medications, and family background to determine whether HRT is appropriate and which formulation and dose minimises your individual risk.
How often should my HRT treatment be reviewed?
Most menopause experts recommend an initial review 6-8 weeks after starting HRT to assess symptom relief and side effects, then annually or as needed. If symptoms aren't adequately controlled, your dose or formulation may be adjusted. Regular reviews ensure your treatment remains effective, safe, and aligned with your changing needs. At UnPause, our AHPRA-registered doctors provide ongoing support and can review your plan during follow-up consultations to optimise your care.
What questions should I ask my menopause expert before starting HRT?
Ask about the type and dose of hormone therapy recommended and why it suits your symptoms and medical history. Enquire about expected symptom relief timelines, potential side effects, and monitoring plans. Ask how long you'll stay on treatment and what happens when you stop. Discuss alternative options if HRT isn't suitable. Ask about your individual risk-benefit profile and how your doctor will adjust treatment if it's not working. At UnPause, our 45-minute consultations are designed to answer these questions thoroughly and support shared decision-making.
Is HRT appropriate for early perimenopause or only for full menopause?
HRT can be used in perimenopause to manage disruptive symptoms like irregular periods, hot flushes, mood changes, and brain fog. Many women benefit from starting treatment early when symptoms first become bothersome, rather than waiting for menopause to be confirmed. Early treatment can improve quality of life and work performance during a demanding life stage. Your menopause expert will assess whether your symptoms warrant HRT now or whether monitoring and non-hormonal strategies are appropriate first.
What are body-identical hormones and how do they differ from other HRT options?
Body-identical hormones (also called bioidentical) have the same chemical structure as estrogen and progesterone your body naturally produces. They're derived from plant sources and processed in a laboratory. Standard pharmaceutical HRT also contains hormones chemically identical to your body's hormones but in regulated, approved formulations. Compounded hormones are custom-mixed by pharmacies and are not regulated by the TGA in the same way. Body-identical and standard pharmaceutical options both undergo rigorous safety testing; compounded options lack this oversight. Discuss which option your menopause expert recommends for your situation.
More from the blog
How to Manage Severe Perimenopause Symptoms
The Hot Flush FilesHow to manage severe perimenopause symptoms: Learn evidence-based strategies to manage severe perimenopause symptoms, from lifestyle changes to treatment
Do Menopause Doctors Listen Well?
The Hot Flush FilesWhy many menopause doctors don't listen — and how to find ones who do. Includes vetting questions, communication strategies, and what to expect.
Personalised Menopause Treatment Plans Online
The Hot Flush FilesDiscover how personalised menopause treatment plans online work. Learn what to expect from telehealth consultations and how to find evidence-based care.